Author: Macenzie Rebelo

From Awareness to Action: What Day Two of the Diabetes Stigma Summit Revealed

Anmol Budhiraja is a mental health and crisis response professional from Toronto, Ontario, whose work is grounded in harm reduction and community advocacy and informed by their lived experience with Type 2 diabetes and caring for loved ones with the condition. As a patient partner and lived-experience research collaborator, they are passionate about challenging stigma, amplifying youth perspectives, and advocating for more equitable healthcare systems, and enjoy spending time with their dog, Drama.

Anmol’s Call to Action: Go beyond performative inclusion and commit to measurable change by ensuring people with lived experience are funded, represented, and empowered to lead in diabetes research, advocacy, policy, and healthcare.

Day Two of the End Diabetes Stigma Global Summit focused on moving conversations beyond stigma awareness and toward real action, accountability, and stigma-free care.

The sessions explored campaigns, communication strategies, advocacy, and community-led approaches that are actively challenging diabetes stigma around the world. 

One session that particularly stood out was the discussion on creative arts and innovation to advance diabetes care and awareness. It was an interactive and deeply human session where people across the globe shared how storytelling, art, design, and innovation can challenge stereotypes and create space for more honest conversations about living with diabetes.

A group of seven diverse individuals smiling and posing together at an indoor event. Behind them is a large stage backdrop featuring a graphic of the Hawa Mahal and text that reads "End Diabetes Stigma Global Summit, Jaipur, India: 28-29 March 2026." The attendees are dressed in a mix of smart-casual and formal attire, wearing event lanyards.
Dynamic minds and global voices uniting for change.

There were also important discussions about international human rights laws and how stigma continues to impact access to care, equity, and quality of life for people living with diabetes. 

The summit closed with conversations focused on next steps and collective action to end diabetes stigma, followed by the #dedoc silent auction and closing remarks from the summit’s visionary partners.

The final video recap of the summit brought the room to tears. There was a powerful mix of gratitude, joy, and sadness as people reflected on what had been created together over the past few days. 

Three things especially stayed with me. 

First, people living with diabetes were visible everywhere in the room, as MCs, speakers, organizers, facilitators, advocates, and participants. Inclusion did not feel performative or like an afterthought. It felt foundational to the entire summit. 

Second, it was refreshing to see new advocates and newly diagnosed individuals being intentionally included in conversations and leadership spaces. Too often, advocacy opportunities are limited to the same voices. This summit created room for growth, mentorship, and community building. 

Third, the emotional atmosphere at the end of the conference reminded me how rare it is for people with lived experience to feel truly seen in healthcare spaces. There was a shared understanding in the room that many people had spent years navigating stigma, judgment, or feeling unheard. 

Why does this matter? Because expertise does not only come from research, policy, or clinical practice. It also comes from living with diabetes every single day.

An over-the-shoulder shot from behind Anmol standing at a white podium, facing a large, seated audience in a grand ballroom. The speaker is wearing a light-colored plaid blazer and a patterned silk headscarf tied at the back. The audience sits at round tables, listening attentively. Overhead, heavy metal stage trusses hold professional event lighting and spotlights beneath a warm, ornately lit ceiling with chandeliers.
Anmol presenting at the End Diabetes Stigma Global Summit.

Meaningfully centering lived experience improves research, strengthens advocacy, informs policy, and ultimately leads to more compassionate and effective care. Diabetes stigma cannot be addressed without the leadership and guidance of the very people who experience it firsthand. 

Something that shifted in me during this summit was a deeper sense of confidence and belonging. Unlike many conferences, this space did not make people with diabetes feel observed or studied. It made them feel trusted. Being surrounded by so many advocates, researchers, healthcare professionals, and community members working toward the same goal made me feel more grounded in the importance of this work.

It reminded me that people living with diabetes are not just patients within a system; they are leaders, experts, and changemakers whose voices carry power. 

As conversations move forward, conferences and organizations must go beyond symbolic inclusion and commit to measurable change.

This includes implementing a 1:1 funding model where, for every funded attendee without lived experience, one person with lived experience is fully sponsored to attend. At least 40 percent of engagement and participation funding should directly support people with lived experience through honorariums, travel, accommodations, accessibility, and childcare.

Conferences should also ensure that at least 60 percent of planning and steering committee members are people with lived experience of diabetes, while reserving leadership roles such as MCs, moderators, and facilitators for community members themselves.

In addition, at least 10 to 15 percent of funded participants should be first-time advocates or newly diagnosed individuals to help build future leadership. 

The End Diabetes Stigma Global Summit showed what is possible when lived experience is not simply included, but trusted, valued, and centered from the very beginning.


Reflections from Day One of the End Diabetes Summit: Who Has the Power, and Who is Stigmatized? 


Matt is a person living with type 2 diabetes. He lives in Toronto, Ontario, and works remotely as a research assistant with the University of Calgary. 

Matt’s Call to Action: Create systems where people with lived experience are not just included in conversations about diabetes but are trusted, respected, and empowered to shape decisions.

My first day at the End Diabetes Stigma Summit was punctuated by several thought-provoking ideas that all relate to an overarching theme: stigma always exists within a power imbalance.

As a person living in a larger body, it was eye-opening to hear that many people of Indian descent tend to have more visceral fat due to cycles of famine that favoured this body type to survive. In Western culture, it seems that being overweight is often framed as a personal failing; something that is very much within one’s power to prevent.

The idea that a person’s genetic predisposition to carry more fat could end up saving their life when food becomes scarce demonstrated to me that not every aspect of obesity needs to be viewed as ‘a problem.’  

Carrot or Stick

The power imbalance that exists between doctors and their patients was emphasized to me in a session discussing diabetes stigma in healthcare.

One doctor on the panel spoke of a time they had scolded their patient regarding their chronic ‘poor’ glucose control. The doctor framed this as an ultimately positive exchange, because more passive forms of encouragement had failed in the past, and berating their patient had motivated them to lower their A1C, ultimately ‘taking their illness more seriously.’

The impression I got from the doctor’s anecdote was that stigma is sometimes an acceptable method of assuring a patient’s compliance.

In a moment of tension, the session moderator called out the doctor, saying something to the effect of ‘it’s never alright to stigmatize others’ and ‘I challenge you to motivate your patients in a way that doesn’t harm their self-esteem.’

Listening Without Hearing  

On a somewhat similar note, in between sessions, I found myself in a “conversation” with another doctor. I put that word in quotations because, while I think of a conversation as consisting of a give-and-take of ideas and opinions, I got the distinct impression that this doctor was primarily interested in what they had to say.

When I mentioned my work on diabetes, obesity, and stigma, the doctor listed off a litany of books and articles that I should read on the topic. Rather than ask me any questions, it seemed to me they were only interested in sharing how well-read they were. This sense of intellectual superiority is something I have experienced from many doctors over the years.

However, I have also known doctors who take the time to really listen to their patients and validate their thoughts and feelings. Doing so actually elevates my faith in their judgment, as no one is so wise that they cannot learn something new from another. 

A group of nine people stand closely together smiling for a photo in a well-lit hotel or conference lobby with polished floors. They are dressed in casual and smart-casual attire, and several are wearing conference lanyards. In the background, modern digital displays feature the website "EndDiabetesStigma.org." Other event attendees can be seen mingling in the blurred background to the right.
Advocacy in Action at the Summit.

Joy in Unexpected Places 

I think the most profound lesson I learned on the first day of the stigma summit was that conferences about tough subjects can also be full of laughter and joy.

The talent show, fashion show, and dance party at the end of the day were much-appreciated respites and a chance for people with lived experience to take centre stage.

Seeing people who have such intense connections to stigma confidently strut their stuff and fearlessly showcase their talents was nothing short of inspiring, and something that could not have happened if participants did not feel safe and supported.

It makes me wonder what else we can achieve as a community when all members are made to feel heard, seen, and empowered.   

Not Another Brick, Rehumanizing Diabetes Beyond Stigma: Reflections from the End Diabetes Global Summit

Mohammed Najeeb Ashraf is a medical communications expert and the CEO of SciVoc Consulting with over 35 years of lived experience with Type 1 diabetes. He brings a deep commitment to advocacy, health equity, and elevating patient voice in science and research.

Najeeb’s Call to Action: Rehumanize diabetes care by seeing and treating people as individuals with lives, identities, aspirations, and experiences beyond their diabetes.

The End Diabetes Stigma conference in Jaipur, India, did not feel like just another addition to the long wall of conferences I have attended over the years. It wasn’t another “brick,” structured, informative, but distant. Instead, it felt like a relief that I didn’t know I needed.

Najeeb stands in front of his AI Chat Bot project and smiles at the camera.
Najeeb Ashraf and Amanda Knight developed an AI Diabetes Technology Chatbot to help people better understand and compare insulin pumps and automated insulin delivery (AID) systems.

I remember sitting in one of the early sessions, listening to a person living with diabetes describe how a routine clinic visit left them feeling judged rather than supported. There was no dramatic confrontation, no overt criticism, no complaints, but just a few words, a certain tone, a subtle shift in body language. Yet the impact lingered with them far beyond that consultation. I found myself thinking about how many such moments we unintentionally create, and how rarely we pause to notice them.

Throughout the conference, many stories like these stayed with me more than any slide or statistic.

In conversations over coffee, in panel discussions, and even in the quiet in-between reflective moments, there was a recurring theme: people were not just managing diabetes, they were managing perceptions.

I recall speaking with a participant who said, almost in passing, “Sometimes the hardest part isn’t the condition, it’s the constant need to explain it.”

That sentence stayed with me long after the conversation ended.

It made me reflect on how easily we default to labels. Terms like “non-compliant” or “uncontrolled” have, at times, found their way into people’s professional vocabulary without much thought. Hearing these lived experiences made me reconsider not just the words themselves, but the assumptions behind them.

What we intend as clinical shorthand can often be received as judgment.

A group of conference attendees stands around a round table displaying a colourful diabetes awareness exhibit. The table is covered with interactive game pieces, educational materials, advocacy signs, and speech-bubble props with messages such as “The Glucose Glitch,” “Diabetes Awareness,” and “Yay for Today.” Participants wear conference lanyards and engage with the display, which highlights diabetes education, advocacy, and lived experiences through creative arts.
Creative arts and advocacy in action.

One moment that particularly stood out was a discussion on language. As the conversation unfolded, I became aware of how well-meaning communication can carry unintended weight. I found myself mentally revisiting past interactions with healthcare practitioners: emails written, discussions led, content developed, and wondering how they did not consider how I might have felt on the other side. It was both uncomfortable and necessary.

Yet, what made the conference truly different was not just the identification of the problem, but the sense of shared responsibility. There was a quiet but powerful acknowledgment that a single group does not create stigma and therefore cannot be addressed in isolation.

I had a brief exchange with a fellow attendee who said, “This isn’t about fixing patients; it’s about fixing the spaces around them.” That perspective felt both simple and profound.

The idea of community came through strongly. In rooms where patients, clinicians, and industry voices came together as equals, something shifted. The hierarchy softened. The conversations became more honest. It made me realize how rare and how necessary such spaces are.

As I left the conference, I found myself thinking less about what I had learned and more about what I needed to unlearn. Ending diabetes stigma is not a campaign or a one-time initiative. It is a continuous process of questioning our language, our assumptions, and the systems we operate within.

This conference was not another brick added to the familiar wall of professional discourse. If anything, it made me see the wall more clearly, how it has been built over time through habits, language, and blind spots. And perhaps more importantly, it made me believe that the work ahead is not about adding more structure but about carefully and intentionally taking parts of it down.

In that sense, Jaipur was a reminder that progress in diabetes care will not be defined solely by innovation or outcomes, but by whether the people at its center feel understood, respected, and truly seen.

And perhaps, that is where the real work begins.

When Intention Creates Connection: Reflections from Night One at the Global End Diabetes Stigma Summit

Brit is a disability and health equity advocate from London, Ontario. As someone living with type 1 diabetes and diabetes-related complications, she speaks openly about how stigma shapes healthcare experiences. She is a Research-to-Action Fellow with Diabetes Action Canada, focused on turning lived experience into action.

Brit’s Call to Action: Create intentional, inclusive spaces that foster connection, belonging, and authentic dialogue, ensuring that lived experience is not only welcomed but valued as a driver of meaningful change.

When I first looked at the program for the Global End Diabetes Stigma Summit, I assumed the Friday evening pre-summit film screening and welcome reception would be fairly quiet. After all, the summit had not technically started yet. 

People were arriving in Jaipur, India, from over 40 countries after long travel days, multiple layovers, delayed flights, and very little sleep. I imagined most people would spend the evening settling in and saving their energy for the packed weekend ahead.

But that’s not what happened.

Every time I looked up, more people had arrived. The room was full, but more importantly, it was engaged. Conversations started almost immediately. It didn’t feel like the usual conference small talk warm-up where everyone politely tests the waters before settling in with the group. 

That’s what captured my attention–this atmosphere didn’t feel accidental.  

ALT for Image: Wide view of a room at the pre-summit film screening discussion, with facilitators speaking to attendees gathered around tables throughout the room.
Even before the summit officially began, the room was already deeply engaged. 

Why Conversations Started Immediately

As the discussions unfolded, I noticed something I often see within the diabetes community. People could describe experiences of stigma very easily, like their experiences had become so familiar that they no longer stopped to examine the weight of them. 

I think many people with lived and loved experience of diabetes become used to functioning this way.

Diabetes can be relentless. You manage the next low or high blood sugar, the next pharmacy or insurance hurdle, the next healthcare interaction that leaves you feeling blamed instead of supported. You explain yourself over and over again, and eventually, many people learn just to keep moving forward because what other choice is there?

But that night felt different.

Conversations moved beyond introductions. People were openly discussing healthcare experiences, burnout, disclosure, food insecurity, supply challenges, and the systems that often fail to meet people where they are. There was very little hesitation.

Later in the evening, my husband joined us for the welcome reception and quietly commented, “Wow, everyone is really welcoming here.” He was right. That observation captured something important: people weren’t wasting energy deciding whether the room was safe to share or not. They already knew it was. And what a wonderful way to begin the summit.

Why the Atmosphere Felt Different

I kept thinking about what made the atmosphere feel so different, and I think the keyword is “intentionality.” 

Before the summit even began, organizers had already established expectations around care, respect, inclusion, and dialogue through the Summit’s Care Protocol. That might sound like a small detail, but I really do not believe it was. It shaped the environment and felt deliberately designed to help people feel safe enough to participate honestly.

It also mattered that the evening centered around films and facilitated dialogue rather than formal presentations. The films weren’t treated like side entertainment before the “real” summit began. Storytelling contributions were one of the abstract submissions for the summit. Storytelling and lived experience were treated as valid, essential forms of knowledge from the very start. 

Watching a film about stigma in a room full of people who understand those experiences creates a very different kind of conversation than watching alone.

The pauses between the films mattered too. People reflected out loud, connected their own experiences to what they had just seen, and built on each other’s thoughts in real time.

Another powerful moment was when Matt Larson, Diabetes Action Canada (DAC) Patient Partner, shared Low Priority, a film about the resilience required to manage diabetes while experiencing homelessness.

Matt appears in the film and helped co-create it with the Calgary Diabetes Advocacy Committee (CDAC), grounding the evening’s conversations in lived experience that’s too often overlooked.

Strong facilitation played a critical role. Linxi Mytkolli, DAC Director of Patient Engagement, created opportunities for people to pause, reflect, and deepen the dialogue, rather than feeling pressured to rush to the next topic.

Nobody seemed eager to leave. In fact, more people kept joining the room as the evening went on.

What This Teaches Us About Patient Engagement

One of my biggest takeaways from that evening was that meaningful engagement does not happen automatically just because people are in the same room. Honest conversations about stigma require intention.

If we want people with lived and loved experience to share openly about difficult topics, we have to create environments where they feel safe enough to do so from the very beginning.

That means: 

  • Clearly communicating care expectations well before events begin 
  • Treating storytelling and arts-based sessions as essential to dialogue– not just as “extra” programming. 
  • Creating time for reflection and facilitated discussion instead of expecting people to process difficult topics alone.

During the summit, Anmol Budhiraja, DAC patient partner, captured this perfectly during his presentation:

“The problem was never that I didn’t have something to say. It’s that no one created the space for me to say it.”

That’s what felt different on Friday night. The summit didn’t just invite people into the room; it also created conditions where people could participate honestly and feel heard. 

And that opening night made something very clear: When you build intentional spaces rooted in care, people show up fully, not because they feel obligated to, but because they feel like they finally can. 

Brit Hancock standing in front of the map of the world. She points to Toronto, Canada on the map while smiling at the camera.

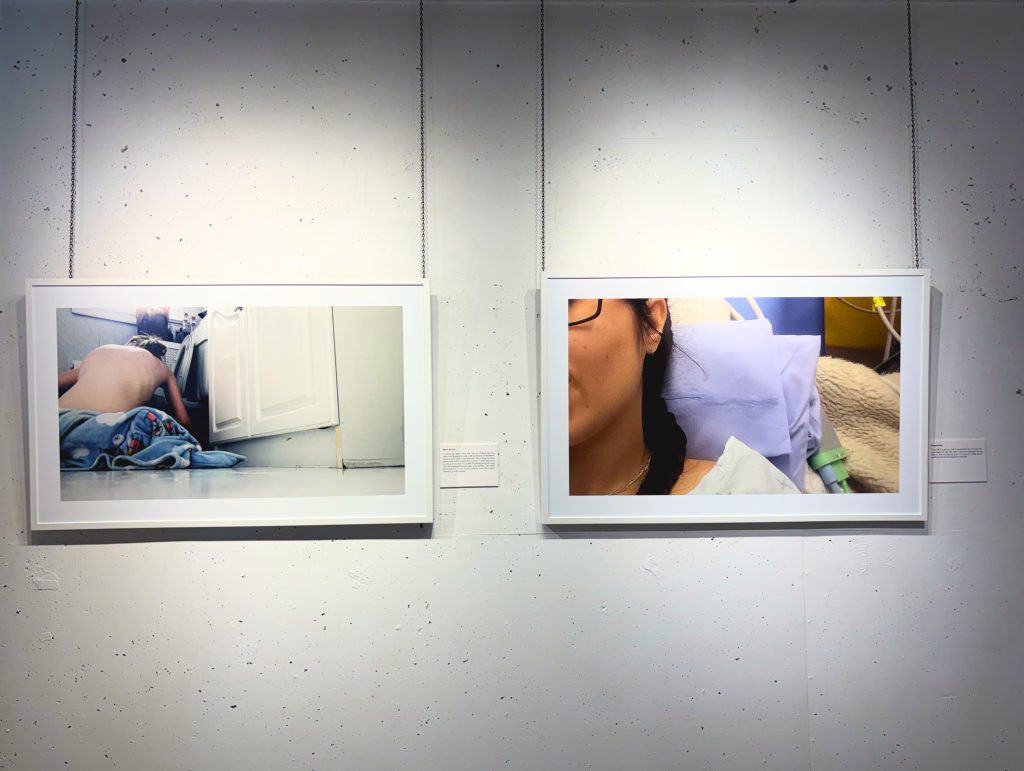
New Photo Exhibition Shares the Untold Everyday Experiences of Young Adults Living with Type 1 Diabetes

Macenzie Rebelo is the Communication and Engagement Associate with Diabetes Action Canada (DAC). She attended the opening of Within the Highs and Lows: Young and Type 1 Photo Exhibition on behalf of DAC. Drawing on her lived experience with an autoimmune condition, she is passionate about advancing equity and inclusion and amplifying community voices to drive meaningful change, particularly through the arts.

In 2019, after a study with parents of young adults living with type 1 diabetes, the research team at St. Michael’s Hospital Diabetes Clinic realized there was still a lot to learn about what it is really like to live with type 1 diabetes as a young adult. 

To better understand the complexities of living with type 1 diabetes and raise public awareness, Unity Health Toronto co-designed a photo exhibition with 22 young adults from diverse backgrounds to share their stories and make sense of their experiences together. 

These conversations created safe spaces for reflection, grief, and connection around the often-overlooked challenges of everyday life with type 1 diabetes. This work began as a pilot project with youth in Ontario and was later expanded nationally through the Canadian Institutes of Health Research. 

After six years of collaboration, the photo exhibit is now open to the public, inviting visitors to immerse themselves in the everyday experiences and challenges of living with type 1 diabetes.  

Through the perspectives of each participant, the photographs explore coming-of-age experiences such as relationships, education, identity, imagining the future, unlearning stigma, and redefining what it means to live well while managing an unrelenting condition that remains woven into their daily lives.  

Each section of the exhibition is organized into zones that represent recurring themes identified through conversations with participants. Each zone is accompanied by supporting raw imagery and audio that surround the public in the sounds, feelings, and visual expressions of living with type 1 diabetes.  

The exhibition is divided into the following zones: 

Zone 1. I’m Greater Than My Highs and Lows: Participants spoke of the constant pressure of numbers – blood sugar highs and lows tracked by clinicians, family, friends, and themselves.  

Zone 2. Walking In a Windstorm – The Unrelenting, The Unpredictable, The Unseen: All participants described diabetes as a constant force. Like walking in a windstorm, life continues forward but never without resistance.  

Zone 3. Diabetes on Display – Surveillance, Stigma and Reclaiming the Narrative: Within the windstorm of daily life with diabetes, surveillance and stigma emerged as shaping forces. 

Zone 4. Network of Care – Health Care Providers: Healthcare professionals emerged as central figures in participants’ accounts, shaping not only clinical care but the broader trajectory of life with diabetes.   

Zone 5. In Relationship with Diabetes – Living with, Against and Alongside: Shaped by forces traced across this exhibit, participants described their relationship with diabetes as continually evolving, marked by moments of tension and tenderness.  

Zone 6. Carry This with You…: When asked what they hoped people would carry forward from this exhibit, participants spoke not only of understanding but of action. They hoped these images and stories would move beyond gallery walls, shaping how people think, speak, and care throughout the world alongside those with type 1 diabetes.  

The art concludes with a reflection wall, inviting visitors to write down what they have learned and anonymously place it on the gallery wall, creating a final, ever-evolving artwork that brings the exhibition to a close. 

Within the Highs and Lows: Young and Type 1 is open to the public from May 29-31 at Arta Gallery, 14 Distillery Lane, Distillery District, Toronto, ON. 

Living With Diabetes Means Living with Loss: New Paper Reframes the Emotional Experience of Diabetes 

A new paper co-authored by Diabetes Action Canada’s (DAC) Linxi Mytkolli argues that diabetes distress may not fully capture the emotional reality of living with diabetes. Instead, that loss and grief are also central, and often overlooked, parts of the experience.  

For decades, the concept of diabetes distress has helped clinicians and researchers better understand the emotional burden of living with diabetes without stigmatization.

But according to the newly published paper in Frontiers in Clinical Diabetes and Healthcare, “Living with what is lost: reframing emotional life with diabetes through an integrative perspective on loss and grief,” there is more to the story.

📖 Read the full paper here

Not only are those living with diabetes navigating burnout, fear of complications, and the demands of self-management, but they are also managing a quieter, more cumulative, and harder emotion to overcome: grief. 

Grief is not tied to a single event, but rather connected to the ongoing experiences of loss that can come with chronic illness, like trust in one’s body, certainty about the future, and a sense of identity. 

While diabetes distress has become an important and widely used framework, the paper examines the emotional burden, frustration, and self-management pressures that those with diabetes face.

The paper introduces a new way of thinking about emotional life with diabetes by applying the Integrative Process Model of Loss and Grief (IPM) to diabetes care and lived experience.

What the researchers wanted to learn

The researchers wanted to explore whether the current language used in diabetes care fully reflects the emotional realities of living with diabetes over time.

While diabetes distress has become an important and widely used framework, the authors argue that it primarily focuses on emotional burden, frustration, and self-management pressures.

What it may miss are the slower, more existential experiences that can unfold across years of living with diabetes:

  • Changes in identity
  • Loss of bodily trust
  • Altered relationships
  • Shrinking possibilities
  • Ongoing adaptation to uncertainty

To explore this, the team applied the Integrative Process Model of Loss and Grief, a framework originally developed in bereavement research, to the experience of living with diabetes.

The model looks at grief across five interconnected dimensions:

  • Physical
  • Emotional
  • Cognitive
  • Social
  • Spiritual

Rather than viewing grief as a temporary response to a single event, the model recognizes that people can experience ongoing and cumulative forms of loss that require continual adaptation.

What the study found

The paper is a conceptual analysis rather than a clinical trial, but it brings together decades of diabetes distress research, grief theory, and lived experience to propose a broader understanding of emotional health in diabetes care.

The authors describe how diabetes can affect nearly every part of a person’s life:

  • Physically, through constant vigilance and fear of complications
  • Emotionally, through burnout, guilt, shame, and exhaustion
  • Cognitively, through relentless planning and mental load
  • Socially, through stigma, misunderstanding, and isolation
  • Spiritually, through questions about meaning, identity, and the future

Importantly, the paper argues that these experiences are not signs of weakness or failure. They are understandable human responses to living with an incurable and demanding chronic condition.

One of the most striking moments in the paper comes from co-author Mytkolli, who reflected during a presentation at the Advanced Technologies & Treatments for Diabetes conference in 2025.

“I grieve my body, I grieve a system that was not built for me. I grieve the future I have to reimagine constantly. Patient engagement is grief work.”

The paper also highlights how these experiences are shaped by broader systems and inequities. In particular, the authors note that for many people, especially those living with type 2 diabetes, emotional burden can be compounded by stigma, food insecurity, limited healthcare access, racism, and social exclusion.

Why this matters

This paper matters because it pushes the conversation about diabetes beyond numbers, targets, and even distress scores.

It offers language for experiences that many people living with diabetes already know intimately but may struggle to describe.

By reframing diabetes through the lens of grief and adaptation, the paper challenges healthcare systems to think differently about emotional support. Instead of viewing difficult emotions as problems to “fix,” the authors encourage clinicians and systems to recognize them as natural responses to ongoing change and uncertainty.

That distinction matters.

It can help reduce stigma, create more compassionate clinical conversations, and support care that recognizes the full human experience of living with diabetes, not just its biomedical markers.

The paper also reinforces a growing recognition within diabetes care that emotional well-being is deeply connected to outcomes, engagement, and quality of life. Emotional burden does not sit outside diabetes care; it is part of it.

For Diabetes Action Canada, the work also reflects a broader commitment to patient partnership and person-centred care. The paper draws directly from grief-literate approaches developed within DAC’s patient engagement initiatives, including co-design methods that recognize emotional labour, vulnerability, reflection, and meaning-making as essential parts of collaboration.

Looking ahead

The authors are clear that this work is not about replacing diabetes distress frameworks or introducing another screening tool.

Instead, they are calling for a broader and more compassionate understanding of emotional life with diabetes – one that creates space for conversations about loss, adaptation, uncertainty, and identity alongside traditional clinical care.

That opens important opportunities for diabetes care, implementation, and patient engagement.

A grief-informed perspective could help healthcare professionals better recognize emotional strain that may otherwise go unspoken. It could support more person-centred conversations in routine care, improve how systems respond to burnout and disengagement, and create safer spaces for people to talk openly about what living with diabetes actually feels like over time.

The paper also points toward practical opportunities to embed grief-literate approaches into patient engagement, education, and implementation work, including the kinds of co-design and partnership models that DAC has helped champion nationally.

Ultimately, the authors argue that acknowledging grief is not about pessimism. It is about making room for the full human experience of chronic illness, and creating care systems that respond with greater understanding, dignity, and connection.

Diabetes Action Canada joins Indigenous-led efforts to advance culturally safe care 

The 2025 Karihwáhstha National Public Policy Circle Gathering, held Dec 8-9, in Wendake, Quebec, brought together Indigenous leaders and partners from across Canada to advance culturally safe, equitable healthcare through Indigenous-led dialogue and action. 

Diabetes Action Canada (DAC) was proud to be part of that work. 

Led by the Indigenous Diabetes Health Circle (IDHC), Karihwáhstha is grounded in Indigenous knowledge, rights and lived experience. The initiative is committed to advancing equitable healthcare for Indigenous Peoples by bringing together leaders and organizations dedicated to Indigenous-led policy development, cultural safety and transformative policy reform. 

The 2025 gathering focused on practical action. Its priorities included fostering a culturally safe and equitable healthcare system through mandatory cultural safety training for healthcare professionals and supporting the meaningful integration of Traditional and Western models of care. 

DAC’s Executive Director, Tracy McQuire, contributed to the initiative as a member of the Karihwáhstha Advisory Committee and DAC’s Director of Patient Partnership; Linxi Mytkolli,was an invited guest. 

Their involvement reflects a much broader relationship between DAC and IDHC, built over many years through shared work in diabetic retinopathy screening, lower limb preservation, and community-led knowledge mobilization. In 2025, DAC and IDHC formalized that relationship through a collaborative relationship agreement grounded in reciprocity, Indigenous-led approaches, culturally competent education, Indigenous data sovereignty, and self-determination.

IDHC continues to shape DAC’s work through its seat on the Steering Committee. The partnership extends to DAC’s Research to Action Fellowship, where IDHC is a partner organization, and most recently at the Global Summit to End Diabetes Stigma in Jaipur, India, where members of IDHC joined DAC in highlighting Canada’s approach to patient and community engagement in diabetes. 

The gathering reinforced the value of collaboration rooted in relationships, shared learning, and action. Through Karihwáhstha, Indigenous leaders and partner organizations are advancing practical, policy-informed approaches to culturally safe and equitable healthcare. 

“It is a real privilege to work closely with IDHC and to be invited into spaces like Karihwáhstha. These are important conversations, and for DAC, being there means listening carefully, learning from Indigenous leaders, and continuing to build the kind of partnership that can support better care,” says Tracy.  

The 2025 Karihwáhstha gathering emphasized the importance of annual collaboration with partners, shared learning experiences and collective action to address systemic inequities in healthcare.

With the establishment of the national gathering in addition to the advisory committee and Karihwáhstha website, purposeful opportunities were created to support relationship-building and continuous knowledge exchange. 

More information about the Karihwáhstha can be found in the Karihwáhstha 2025 National Public Policy Circle Gathering Dialogue and Action Summary. 

  • 1
  • 2